
Retatrutide weight loss 2026 research has attracted attention after new Phase 3 results reported substantial average reductions in body weight.
Updated: 1 October 2026
Retatrutide has been talked about online for several years as a possible “next-generation” weight-loss injection. Until recently, however, much of that excitement came from early-stage research.
That has now changed.
On 29 September 2026, researchers published major Phase 3 results in the New England Journal of Medicine. In the study, adults with obesity who did not have diabetes received retatrutide or placebo once a week for 80 weeks.
At the highest studied dose, the average reduction in body weight was 25.0%, compared with 3.9% with placebo.
That is an attention-grabbing result, but it needs context.
Retatrutide is still an investigational medicine. It is not currently authorised for routine public use in the UK, and the Medicines and Healthcare products Regulatory Agency (MHRA) has specifically warned people about unlicensed retatrutide being sold online.
So what did the new research actually find? How does retatrutide differ from medicines such as Mounjaro? What side effects were reported? And could it eventually become another option for obesity treatment?
Here is what the evidence tells us so far.
What is retatrutide?
Retatrutide is an experimental once-weekly injectable medicine being developed by Eli Lilly.
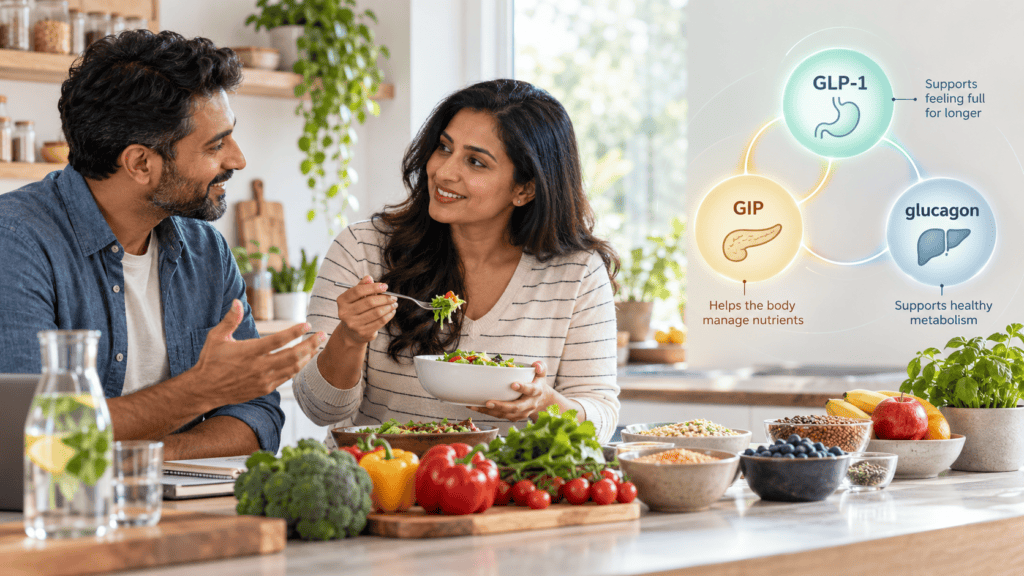
Its scientific interest comes from the fact that one molecule activates three different hormone receptors:
- GLP-1
- GIP
- glucagon
This is why researchers describe retatrutide as a triple hormone receptor agonist.
You may sometimes see it called a “GLP-3” drug online. That name is misleading. There is no new hormone called GLP-3 involved here. The more accurate description is a GLP-1/GIP/glucagon triple agonist.
GLP-1 and GIP are involved in appetite, glucose regulation and signals related to eating. Glucagon has several metabolic effects, including effects on glucose and energy metabolism.
The idea behind retatrutide is therefore different from simply increasing the strength of a traditional GLP-1 medicine. Researchers are investigating whether targeting several metabolic pathways together can produce greater effects on body weight and metabolic health.
This does not automatically make it better or safer. That has to be demonstrated through properly controlled clinical trials.
And that is why the newly published Phase 3 evidence matters.
What did the new Phase 3 retatrutide study find?
The new study, called TRIUMPH-1, was a Phase 3 randomized, double-blind clinical trial.
A total of 2,339 adults with obesity without diabetes were randomly assigned to receive either:
- retatrutide 4 mg
- retatrutide 9 mg
- retatrutide 12 mg
- or placebo
Treatment continued for 80 weeks.
The study was published in the New England Journal of Medicine on 29 September 2026.
The average percentage changes in body weight were:
| Treatment | Average weight change at 80 weeks |
|---|---|
| Retatrutide 4 mg | −17.6% |
| Retatrutide 9 mg | −23.7% |
| Retatrutide 12 mg | −25.0% |
| Placebo | −3.9% |
The differences between the higher retatrutide doses and placebo were statistically significant.
These are substantial average reductions.
However, there is an important word in that sentence: average.
A result of 25% does not mean that everybody taking retatrutide lost exactly one-quarter of their body weight. Individual responses to obesity medicines can vary considerably.
Clinical trial results also come from carefully selected participants who are regularly monitored and treated according to a study protocol.
They should not be interpreted as a guarantee of what an individual person would experience in routine healthcare.
Retatrutide also affected obesity-related health problems
TRIUMPH-1 was particularly interesting because researchers looked beyond the number on the scales.
Among the participants were:
- 574 people with knee osteoarthritis
- 243 people with obstructive sleep apnoea
Researchers reported improvements in knee osteoarthritis pain and reductions in sleep-apnoea events among participants receiving retatrutide compared with placebo.
That does not necessarily mean retatrutide directly “treats” every obesity-related condition.
Some improvements may be connected to substantial weight loss, while other metabolic effects are still being studied.
But it reflects an important change in obesity research.
Modern obesity trials are increasingly examining whether treatments improve health complications associated with excess weight, rather than focusing only on kilograms lost.
Retatrutide is now being investigated across several obesity-related conditions and outcomes.
A description of the wider TRIUMPH Phase 3 programme published in Diabetes, Obesity and Metabolism explains that the programme includes studies involving obesity, obstructive sleep apnoea and knee osteoarthritis, as well as other related health risks.
What about people who have type 2 diabetes?
Another important Phase 3 study was published in The Lancet on 29 September 2026.
TRIUMPH-2 studied 1,152 adults with obesity or overweight and type 2 diabetes.
Participants received retatrutide at 4 mg, 9 mg or 12 mg, or placebo.
After 80 weeks, average weight changes using the study’s treatment-regimen analysis were approximately:
- −11.9% with 4 mg
- −16.8% with 9 mg
- −18.8% with 12 mg
- −5.1% with placebo
Researchers also reported improvements in blood-glucose control.
You may see slightly different percentage figures for this trial in press releases. This can happen because clinical trials can use different statistical approaches — known as estimands — to answer slightly different questions about treatment effect.
For readers, the important message is simpler:
People with type 2 diabetes also experienced substantial average weight loss, but the results were not identical to those seen in people without diabetes.
This is another reason we should not take one headline percentage and assume it applies to everybody.
Retatrutide vs Mounjaro: what is the difference?
Retatrutide and Mounjaro are related to the same modern area of metabolic medicine, but they are not the same drug.
Mounjaro contains tirzepatide.
Tirzepatide activates two receptors:
GIP + GLP-1
Retatrutide activates three:
GIP + GLP-1 + glucagon
The NHS describes tirzepatide as a dual GLP-1/GIP agonist used to manage type 2 diabetes or obesity in appropriate patients.
Retatrutide adds activity at the glucagon receptor.
That third pathway is one reason researchers are so interested in the drug.
But it would be misleading to look at the 25% figure from TRIUMPH-1 and simply declare:
“Retatrutide is better than Mounjaro.”
That conclusion cannot be made reliably from separate studies.
Different trials may involve different:
- patient populations
- eligibility criteria
- starting weights
- treatment lengths
- lifestyle programmes
- statistical methods
- rates of treatment discontinuation
A proper head-to-head randomized trial provides much stronger evidence for comparing two treatments directly.
Until those comparisons are available, percentages from unrelated trials should be interpreted cautiously.
For a wider explanation of currently available injections, read our Majra Health guide:
Mounjaro Weight Loss: Is It Safe & Worth It in 2026?
You can also read:
GLP-1 Weight Loss Guide: Safe Use, Diet & Real Results
What side effects have been reported with retatrutide?
Large weight-loss numbers naturally attract attention, but effectiveness is only one side of a medicine.
Safety and tolerability matter just as much.
In the new TRIUMPH-1 Phase 3 study, the researchers reported that the most common adverse events were gastrointestinal.
The separate TRIUMPH-2 trial gives us more detailed information.
Among participants with obesity and type 2 diabetes, common gastrointestinal problems included diarrhoea and nausea.
For example, diarrhoea was reported in around:
- 27% of people receiving 4 mg
- 34% receiving 9 mg
- 34% receiving 12 mg
- 13% receiving placebo
Nausea occurred in approximately:
- 14% with 4 mg
- 21% with 9 mg
- 28% with 12 mg
- 8% with placebo
The investigators described the overall safety profile as generally consistent with medicines that have GLP-1 receptor activity.
Some participants discontinued treatment because of adverse events.
This is worth remembering whenever a weight-loss trial is reduced to a single impressive percentage.
A medicine can produce strong average results while still being unsuitable or difficult to tolerate for some individuals.
Longer-term safety information will also continue to matter if retatrutide eventually reaches routine clinical use.
Is retatrutide approved in the UK?
No.
As of 1 October 2026, retatrutide is not authorised for routine public use in the UK.
Eli Lilly also states that retatrutide remains investigational and has not yet been approved by a regulatory agency.
This is very different from tirzepatide.
Mounjaro is a licensed prescription medicine in the UK for approved indications, including obesity in eligible patients. The MHRA lists tirzepatide among authorised medicines used for diabetes and weight management.
Retatrutide should therefore not currently be treated as another commercially available weight-loss injection.
Can you buy retatrutide online?
This is where the situation becomes particularly important.
Although retatrutide has not been authorised in the UK, products claiming to contain it have appeared through websites, social media sellers and other unofficial sources.
The MHRA has issued a very clear warning.
It states that retatrutide has not been authorised for use in the UK, and products being sold outside legitimate clinical research cannot be assumed to have been properly tested for quality, safety or effectiveness.
UK authorities have also taken enforcement action against illegal manufacturing and distribution operations involving products labelled as retatrutide and other weight-loss medicines.
The problem is not simply whether an unofficial product “works.”
With an unregulated injectable product, you may not reliably know:
- what substance is actually inside
- whether the stated dose is accurate
- whether it has been manufactured under appropriate sterile conditions
- whether it contains contaminants
- whether it has been stored correctly
That makes buying supposed retatrutide from unofficial internet sellers very different from receiving an authorised prescription medicine from a regulated healthcare service.
Is retatrutide the same as “GLP-3”?
No.
This is becoming a surprisingly common search term.
“GLP-3” is not the proper scientific name for retatrutide.
Eli Lilly itself explains that the nickname is scientifically inaccurate.
Retatrutide targets three receptors — GIP, GLP-1 and glucagon — which is why the proper description is a triple agonist.
It may sound like a small wording issue, but accurate terminology matters.
Calling it GLP-3 can create the false impression that scientists have discovered a new GLP hormone called GLP-3.
They have not.
Does 25% weight loss mean retatrutide could replace bariatric surgery?
This is another conclusion that should not be made from the current evidence.
The average weight loss reported at the highest dose in TRIUMPH-1 is substantial.
But medicines and bariatric surgery are fundamentally different treatment approaches.
Choosing between lifestyle treatment, medication and metabolic or bariatric surgery depends on much more than a single average weight-loss percentage.
Doctors may consider factors such as:
- degree of obesity
- diabetes
- cardiovascular risk
- sleep apnoea
- mobility
- previous treatment
- other medical conditions
- medicine tolerance
- long-term risks and benefits
- individual preferences
Long-term durability also matters.
An 80-week trial tells us a great deal, but people living with obesity may require management over many years.
We still need more evidence about what happens with retatrutide over longer periods and what happens when treatment is discontinued.
Why could retatrutide produce substantial weight loss?
Scientists are still investigating the exact contribution of each receptor.
GLP-1 signalling is well known for influencing appetite, food intake and glucose regulation.
GIP also has metabolic and insulin-related effects and forms part of the mechanism of tirzepatide.
Retatrutide then adds glucagon receptor activity.
Glucagon is traditionally associated with increasing blood glucose, which may initially make its inclusion sound unusual.
However, glucagon signalling also has effects on energy expenditure and metabolism.
The scientific concept is therefore to balance several hormonal effects within one molecule.
Earlier Phase 2 research had already suggested that this approach could produce substantial reductions in weight.
In a Phase 2 obesity trial published in 2023, retatrutide produced dose-dependent reductions in body weight over 48 weeks.
The new Phase 3 evidence is important because it tests the medicine in much larger populations and at a later stage of clinical development.
Is retatrutide coming to the UK soon?
There is currently no confirmed UK launch date.
This is an area where online articles can easily move from evidence into speculation.
Lilly says retatrutide remains under clinical investigation, and public availability depends on completion of the development programme and regulatory review.
The company said in July 2026 that it planned to submit a regulatory application to the US FDA in the first quarter of 2027.
A planned US submission is not the same as UK approval.
UK availability would require the relevant regulatory process, and decisions around NHS use would involve additional considerations.
Until official UK regulatory decisions are made, claims giving a definite UK release date should be treated cautiously.
What we still don’t know about retatrutide
Despite the impressive Phase 3 results, several questions remain.
1. Long-term safety
Clinical trials provide carefully collected safety information, but larger numbers of patients and longer periods of use can sometimes reveal uncommon problems that were difficult to identify earlier.
2. What happens after treatment stops
Weight regain after stopping obesity medication is an important issue across this field.
Long-term studies will help determine how weight changes after retatrutide is discontinued and whether ongoing treatment is usually required.
3. Cardiovascular and kidney outcomes
Weight loss is useful, but researchers also want to know whether treatments reduce major health events such as cardiovascular and kidney complications in relevant populations.
Retatrutide is being investigated further across cardiometabolic outcomes.
4. Real-world effectiveness
Clinical trials involve regular monitoring and carefully controlled protocols.
Real-world results may not perfectly match clinical trial averages.
5. How it compares directly with existing treatments
Separate clinical trials cannot provide the same certainty as a head-to-head comparison.
This will be particularly important when people begin comparing retatrutide with established treatments such as tirzepatide or semaglutide.
What should people do right now?
For most readers, the practical message is straightforward.
Retatrutide is one of the most interesting medicines currently being studied for obesity, and the latest Phase 3 evidence strengthens the scientific case for it.
But interesting does not mean approved.
Anyone considering medical treatment for obesity should discuss appropriate licensed options with a qualified healthcare professional rather than attempting to obtain experimental medicines through unofficial sources.
In the UK, authorised weight-management medicines are prescription-only and should come through appropriately regulated healthcare and pharmacy services.
Lifestyle also remains part of obesity management even when medication is used.
Nutrition, physical activity, sleep, muscle maintenance and management of existing health conditions still matter.
If you are trying to understand why your weight is not changing despite eating less, you may also find this Majra Health article useful:
Why You’re Not Losing Weight Even When You Eat Less
Frequently Asked Questions
Is retatrutide approved in the UK?
No. As of 1 October 2026, retatrutide is not authorised for routine public use in the UK. It remains an investigational medicine.
How much weight did people lose with retatrutide?
In the new Phase 3 TRIUMPH-1 trial involving adults with obesity without diabetes, average weight reductions after 80 weeks were 17.6%, 23.7% and 25.0% with the 4 mg, 9 mg and 12 mg doses respectively, compared with 3.9% with placebo. Individual results varied.
Is retatrutide stronger than Mounjaro?
The drugs work differently: Mounjaro/tirzepatide targets GIP and GLP-1, while retatrutide targets GIP, GLP-1 and glucagon. Results from separate studies should not be used to declare one drug superior without appropriate direct comparative evidence.
Is retatrutide a GLP-1?
It includes GLP-1 receptor activity, but it is more accurately described as a triple GIP/GLP-1/glucagon receptor agonist.
Is retatrutide GLP-3?
No. “GLP-3” is an informal and scientifically inaccurate nickname. Retatrutide targets three different receptors; it does not act on a hormone called GLP-3.
Can I buy retatrutide online in the UK?
Retatrutide is not currently authorised for UK public use. The MHRA warns against products claiming to contain retatrutide being sold through unregulated sources.
What are the most common retatrutide side effects?
Gastrointestinal problems have been among the most commonly reported adverse events. In Phase 3 research these included nausea and diarrhoea, with frequency differing by dose.
When will retatrutide be available?
There is no confirmed UK availability date. Regulatory review must take place before it could become a routinely available medicine.
The bottom line
Retatrutide has moved beyond being simply an exciting early-stage weight-loss drug.
The newly published Phase 3 evidence is substantial.
In 2,339 adults with obesity without diabetes, the highest studied dose produced an average 25.0% reduction in body weight over 80 weeks, compared with 3.9% with placebo.
Another Phase 3 trial has also reported substantial weight reduction and improved glycaemic control among adults with obesity or overweight and type 2 diabetes.
That makes retatrutide one of the most closely watched investigational obesity medicines of 2026.
But there is an equally important second half to the story:
retatrutide is still experimental.
It is not currently approved for public use in the UK. Long-term safety, durability, real-world effectiveness and several major health outcomes continue to be studied.
The scientific results deserve attention.
The online hype deserves caution.
That distinction matters.
Sources
New England Journal of Medicine — TRIUMPH-1 Phase 3 study
Read the original NEJM study
PubMed — TRIUMPH-2 Phase 3 study in obesity and type 2 diabetes
Read the PubMed record
UK Medicines and Healthcare products Regulatory Agency (MHRA)
Read the MHRA warning on retatrutide and unlicensed weight-loss medicines
NHS — Tirzepatide/Mounjaro information
Read NHS guidance on tirzepatide
Eli Lilly — Current retatrutide development status
Read Lilly’s retatrutide information
Medical disclaimer: This article is for general information only and is not a substitute for individual medical advice.

Vipin Sharma is a UK-based Food Technologist and wellness-focused content creator with over 5 years of experience in food safety, nutrition awareness, and quality assurance within regulated food environments. He shares research-backed health insights to help people make informed lifestyle and diet choices.
His work focuses on translating complex nutrition and health information into simple, practical guidance that can be applied in everyday life. His content is informed by scientific literature, public health guidance, and real-world industry experience.
Vipin promotes a balanced, evidence-based approach to wellness, encouraging sustainable habits and long-term health rather than quick-fix solutions.